Category Archives: Athletic Training

Atrial Fibrillation at Altitude

By Ellie Himyak, PA-S

Atrial fibrillation is the most commonly diagnosed chronic heart arrhythmia in the United States, with prevalence rising due to an aging population1 . It is characterized by an abnormality in the electrical activity in the top chambers of the heart, or atria, causing the heart muscle to “fibrillate” instead of producing an effective contraction. This uncoordinated electrical activity can lead to very fast atrial heart rates up to 300-500 beats per minute 1 . Due to the lack of effective atrial contraction, the ventricular response is subsequently irregularly irregular and can be rapid in rate as well. Atrial fibrillation is classified based on persistence2 :

  • Paroxysmal: abnormal rhythm terminates spontaneously or with intervention within 7days of onset
  • Persistent: Abnormal rhythm is sustained for 7 days or more
  • Long-standing persistent: Abnormal rhythm is continuous for 12 months or more with a rhythm-control strategy pursued
  • Permanent: Abnormal rhythm is continuous and the decision has been made by both patient and provider to stop attempts to restore a normal rhythm

Patients with atrial fibrillation experience a wide variety of symptoms. Some people may be completely asymptomatic to the arrhythmia, while others may experience an array of symptoms including fatigue, palpitations, shortness of breath, dizziness, loss of consciousness, and heart failure symptoms. Timely diagnosis of atrial fibrillation is important to mitigate the complications associated with the arrhythmia. One of the main complications that need to be addressed is the increased risk of stroke . Due to the discoordination of atrial electrical activity, blood is not effectively pumped through the heart. Stagnation of blood results in an increased risk of blood clot formation. These can then travel to the brain and cause a stroke. Given this risk, those who are diagnosed with atrial fibrillation are commonly started on anticoagulation (blood thinning) medication to reduce the risk of clot formation. Uncontrolled atrial fibrillation can also increase the risk of heart failure. This is especially common when the arrhythmia is associated with a rapid ventricular heart rate.
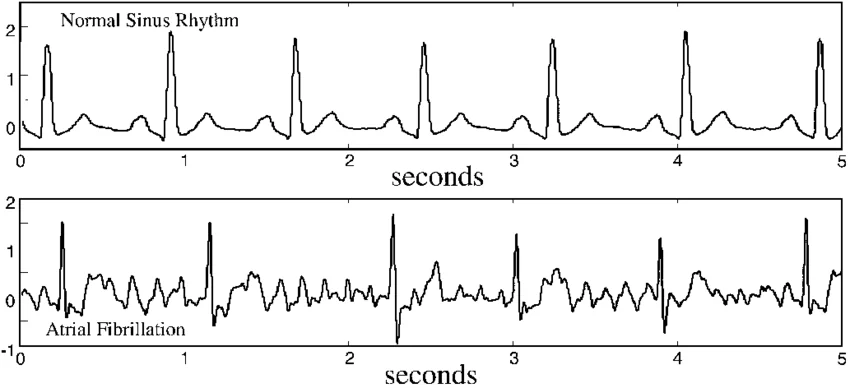
Two charts depicting a normal sinus rhythm by spikes in seconds over an atrial fibrillation depicting more frequent, intense spikes per second.

There are many etiologies of atrial fibrillation with a mixture of genetic, environmental and metabolic components. Family history, genetic predisposition, and advanced age increase the risk of developing atrial fibrillation, however there are several other environmental and metabolic factors that can contribute to the development of this arrhythmia. Underlying cardiac/structural abnormalities including history of heart failure, coronary artery disease, valvular heart disease, and congenital heart disease can increase the risk of atrial fibrillation. Additional risk factors include hypertension, sleep apnea, obesity, diabetes mellitus, excessive alcohol use, and smoking.

This blog post aims to reflect upon the impact of high altitude on cardiac arrhythmias like atrial fibrillation. Unfortunately, there is very limited data on the direct relationship between atrial fibrillation and residence at high altitude. Current data suggest that high altitude environments do not directly cause atrial fibrillation, but there is evidence that the hypoxicenvironment of high-altitude areas can create strain on the heart and exacerbate underlying heart conditions3. Those who have been previously diagnosed with heart conditions, including atrial fibrillation, should be aware of the effects of traveling to high altitude, especially if they plan to participate in heavy exertion4.

To gain some perspective on this topic, Jim Brooks, a member of the Summit County community in Colorado, contributed a personal account of his experience with living with atrial fibrillation at high altitude. Jim moved to Colorado at the age of 56 and was diagnosed with atrial fibrillation 9 years later. Jim explained that he was initially diagnosed while on a trip to Denver, when he noticed something felt “different” in his heart. He presented to the emergency department and was found to be in an abnormal rhythm called “atrial flutter” which is an abnormal heart rhythm with a similar underlying pathophysiological mechanism to atrial fibrillation. The two abnormal rhythms commonly interconvert. Jim was later diagnosed with atrial fibrillation as well.

Following his diagnosis, Jim underwent thorough cardiac evaluation to evaluate the classification of his arrhythmia and to ensure he had maintained stable heart function. Included in this workup was a sleep study which revealed that Jim had been living with severe uncontrolled sleep apnea. Sleep apnea is a very common risk factor for atrial fibrillation. Apneic events are events during the night in which a person’s breathing pauses, which creates hypoxia and ultimately increases strain on the heart. There is evidence that living at altitude increases the risk of developing sleep apnea with an estimated 1.5-fold increase in risk per 1,000m of elevation gain5. For those who have a diagnosis of sleep apnea, traveling or moving to higher elevation can exacerbate this issue and require adjustments to treatment.

A man in sunglasses takes a selfie from the top of a rocky mountain peak with the mountain ridge extending in the background toward a large lake surrounded by mountains and covered in pine forests.

Jim is doing quite well and states that he does not feel limited by his atrial fibrillation. Jim’s sleep apnea is treated with nocturnal supplemental oxygen, and his atrial fibrillation is controlled with medication. Jim continues to be able to engage in all the activities he enjoys doing including hiking and skiing. When asked what advice he received from his cardiologists regarding living with this heart arrhythmia at altitude, Jim highlighted the importance of hydration. He was told that as we age, especially men, can have a decrease in their sense of thirst, so he is very mindful about pre-emptively hydrating, especially if he plans to engage in activities requiring exertion.

Jim also prioritizes a healthy diet and prefers to avoid alcohol and caffeine as these are known potential triggers to atrial fibrillation.
Upon his closing remarks, Jim highlighted the importance of health monitoring for populations living at altitude, especially oxygen monitoring. He believes that everyone over the age of 50 living at altitude should at the very least own a pulse oximeter to evaluate for low oxygen readings, and importantly, that there is technology available today which can monitor for fluctuations in oxygen levels overnight which may prompt a conversation with a medical provider to pursue formal testing to evaluate for sleep apnea. Jim is grateful for the care he has received here in Summit County. He expressed his support and excitement for on-going high altitude research.

  1. Baman JR, Passman RS. Atrial Fibrillation. JAMA. 2021;325(21):2218 ↩︎
  2. Joglar JA, Chung MK, et al. 2023 ACC/AHA/ACCP/HRS Guideline for the Diagnosis and Management of Atrial Fibrillation: A report of the American College of Cardiology/American Heart Association Joint Committee on Clinicacl Practice Guidelines. J Am Coll Cardiol. 2024;83(1):109-279 ↩︎
  3. South Denver Cardiology. Does High Altitude Trigger ATrial Fibrillation (A-fib)? South Denver Cardiology August 6, 2024. Accessed September 29, 2026 ↩︎
  4. Cornwell WK, Baggish AL, Bhatta YKD, et al. Clinical implications for exercise at altitude among individuals with cardiovascular disease. J Am Heart Assoc. 2021;10(19):e023225 ↩︎
  5. Huang, Y., Jia D., Jiang, Q. et al. Exercise capacity of patients with obstructive sleep apnea at moderate to high altitude. Sleep Breath. 30, 281(2026) ↩︎

UPDATE FROM ENGLAND: INTERNATIONAL SOCIETY OF MOUNTAIN MEDICINE CONFERENCE

Dr Chris was invited to present a poster : “Chest X-ray Findings on 139 Hypoxic Children at High Altitude” in the Peaks District three hours north of London. She also gave a presentation with slides to the assembly of over 200 doctors from around the world-Japan to Kyrgyzstan. She introduced our book “Surviving and Thriving at Altitude” in the section on mountain literature and addressed a small group with an overview of conditions she sees in children at altitude. The meeting was held in a tent with the participants in their puffy jackets carrying their backpacks.

Speakers covered topics relevant to mountain living including “Women at Altitude”, “Children at Altitude”, hypoxic training for athletes, REDs: relative energy deficiency syndrome, climate change, hypothermia, frostbite, and more.

A concern here in Colorado with so many world class athletes, especially adolescents, is the balance between calories burned and calories needed for maximum muscle development and performance. REDs affects every system in the body, from sleep to mental and physical well-being. German orthopedic and trauma surgeon Volker Schoffl works with Olympic athletes using a questionnaire for initial screening, blood tests and physical exam to establish the diagnosis. A team of psychologists, nutritionists and physicians determine and implement treatment.

Experts from The Altitude Centre in London, James Barber and Dr. Patrycja Jonetzko, a cardiothoracic anesthesiologist, described programs to prepare athletes competing in low oxygen environments. Using equipment to create a hypoxic environment such as face masks and tents, they expose subjects for various lengths of time from minutes to hours during the weeks leading to the event. They described progress towards individualized targeted programs to increase mitochondrial efficiency.

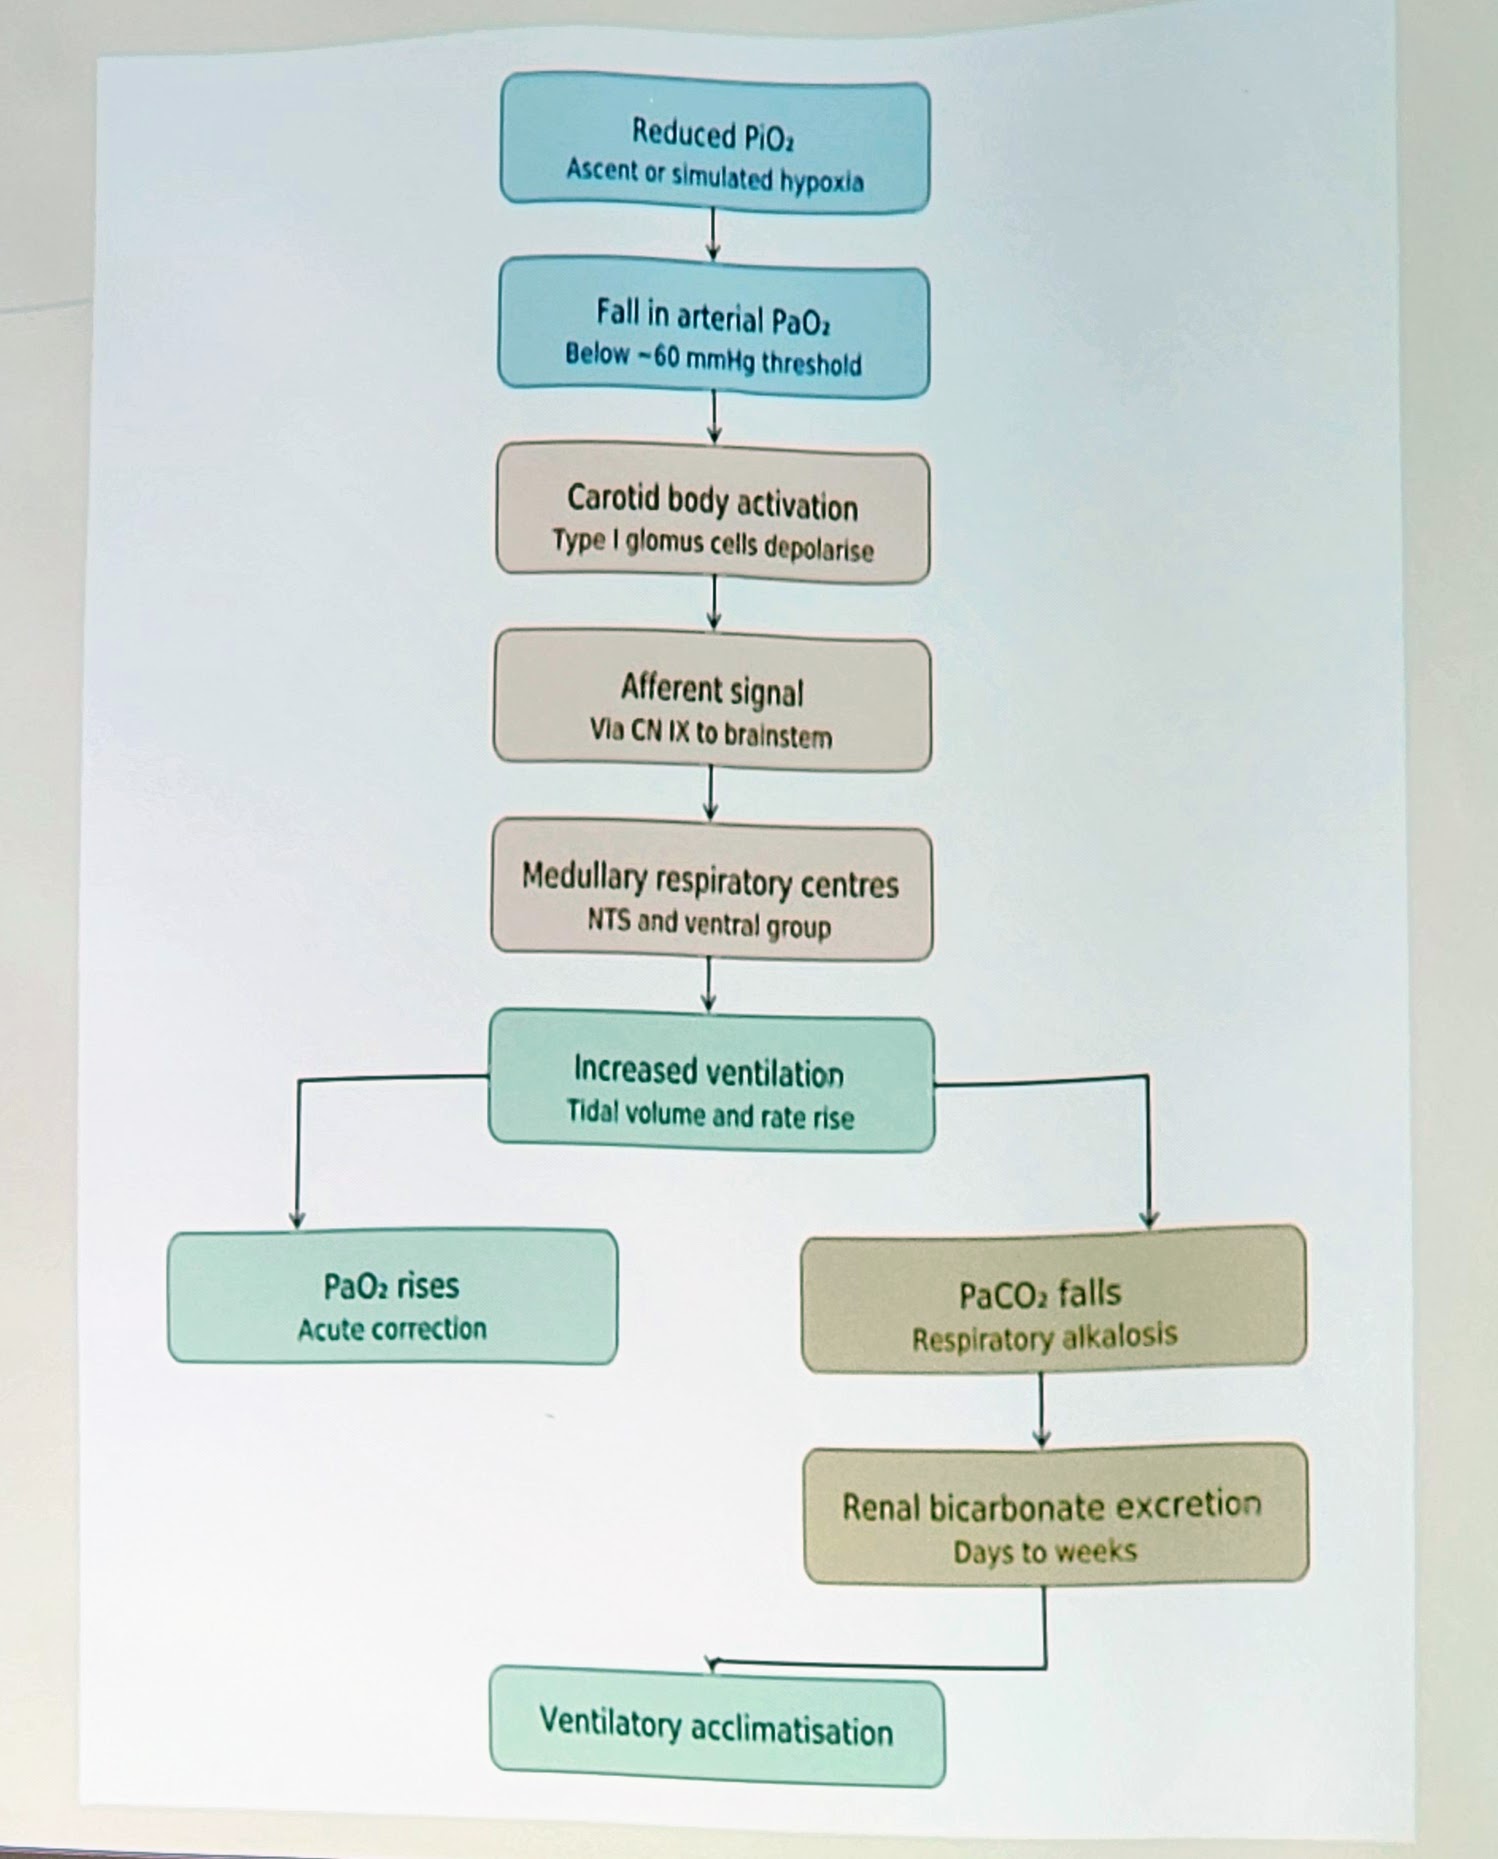
Physiology of altitude adjustment

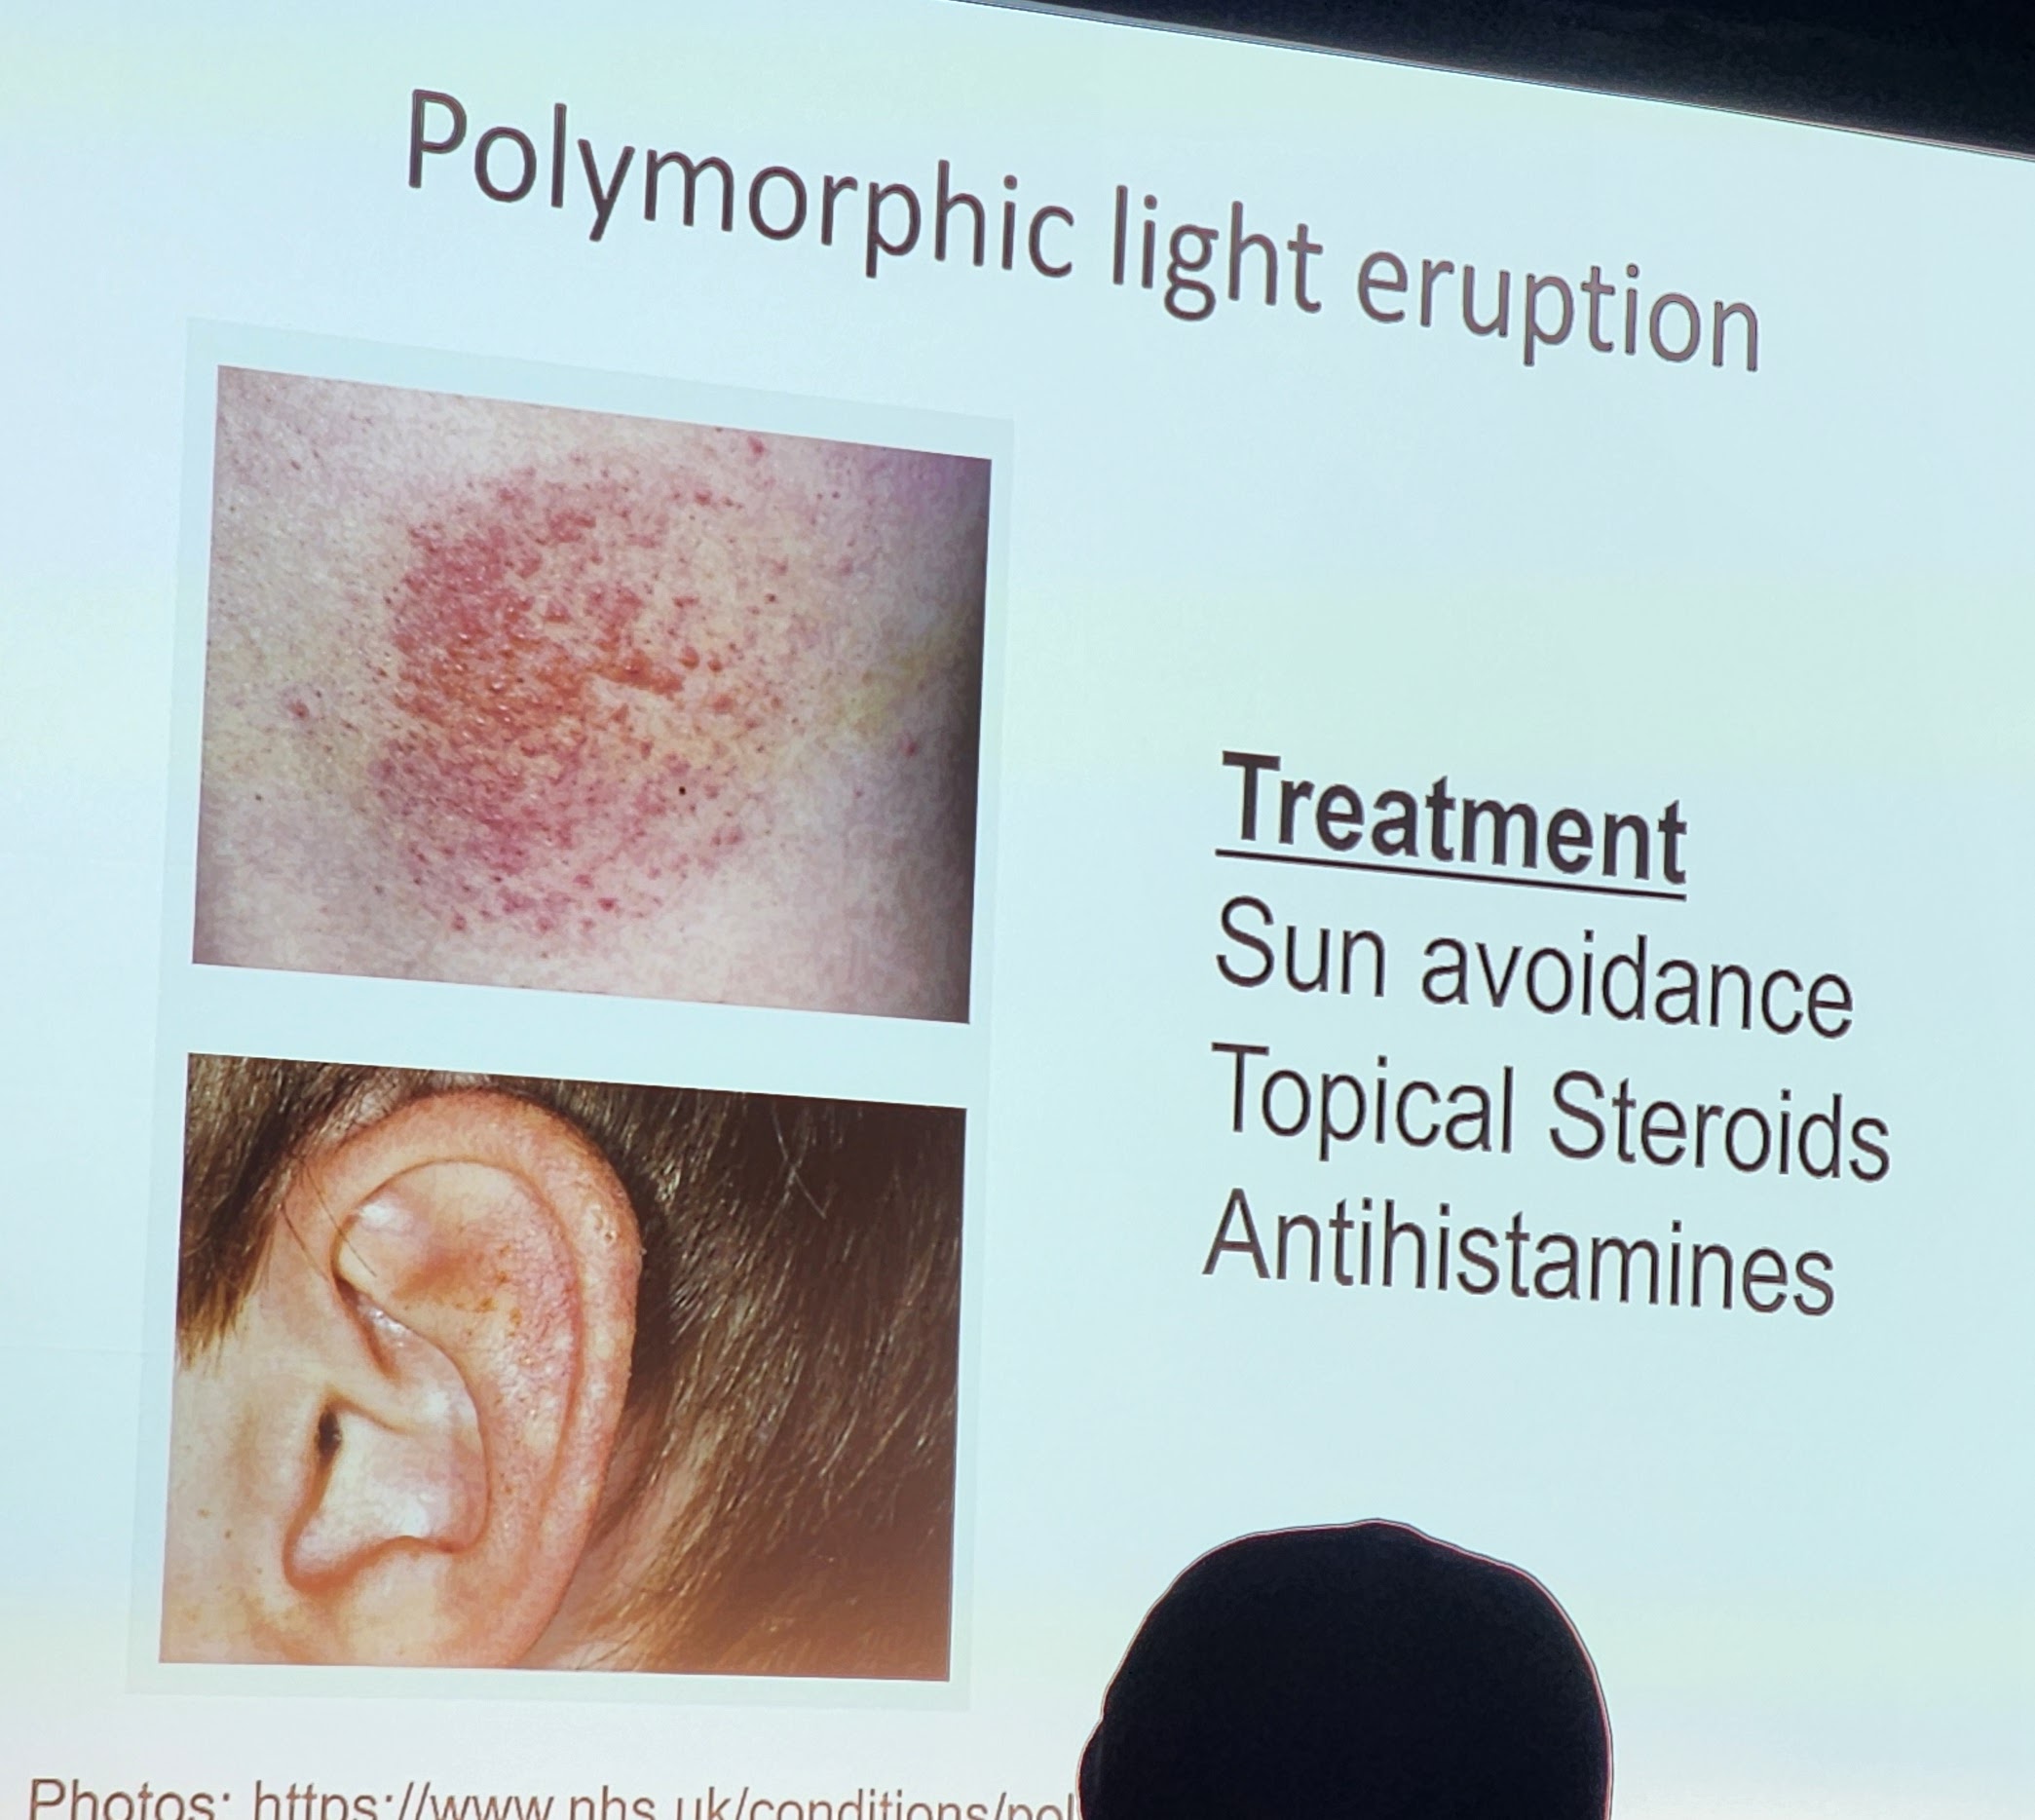
Dr Deborah Miller spoke during the section on “Children at Altitude” . She had just spent three months working as a pediatrician in Saipan in Micronesia where we first met. Her altitude expertise comes not only from several rotations in remote mountain clinics but personal experience with altitude illness in her children in Nepal and Colorado. She described her experience at the HRA Clinic in Nepal, at 14,300 ft. Her talk included environmental exposures with descriptions of sun toxicity. Ultraviolet radiation exposure is increased by 90% due to reflection of light from snow compared to 15-30% from sand or 5-20% from water. Treatment is similar to that for hives with antihistamines and topical steroids.

Dr Miller shared guidelines for estimated walking distances with children from momgoescamping.com. Start with ½ mile per year of age, reduce by 50% for steep elevation, increase by 10% if the destination is of interest to the child and by 25-50% if they have friends along.  Now for the pack: decrease distance by 10% while assuming you will end up carrying it, and another 10% if you have a heavy pack.

The final and most important points from both her and Dr. Chris’ experience about children visiting altitude are:

  1. Previous excellent altitude performance does not always predict future performance
  2. Recent illness can play a role (and make them more susceptible to altitude illness)
  3. Emergency plans are important
  4. HAPE can take a long time to fully resolve

The day devoted to frostbite and hypothermia highlighted the importance of international registries and cooperation for progress in these devastating conditions. Although Canada, Alaska and Scandinavia have many cases the group leading investigations is based in Minnesota, where extremely cold winters and homelessness create conditions that make frostbite and hypothermia common. Rachel Nygaard, PhD discussed her work in this field.

There were fascinating and complex discussions about how and when to combine the various drugs used for resuscitation from cardiac arrest in hypothermia and the vasodilators for frostbite.  Of course, there was emphasis on the universal adage that “no one is dead until they are warm and dead”, citing cases of cardiac arrest for over 2 hours with full recovery.

There were many more interesting sessions and much informal learning and networking. Dr. Chris was reacquainted with physicians who remembered her presentations at conferences in Telluride in 2016, Snowbird in 2024 and Lake Louise in 2025.

Support sharing information and promoting research through the nonprofit Summit High Altitude Information & Research.

Pressure as Prevention: Can Hyperbaric Oxygen Help You Beat Altitude?

Pictured above is the highest hyperbaric chamber in the world at the Bolivian Naval Station at Lake Titicaca.

If you’ve ever climbed high enough to feel short of breath, dizzy, or just “off,” you’ve likely experienced the effects of high altitude on the human body. Once you get above about 2,500 meters (8,200 feet), the air gets “thinner”—not because oxygen disappears, but because there’s less pressure pushing oxygen into your body. This particular problem is termed hypobaric hypoxia, and it can turn a beautiful mountain adventure into a medical problem quickly.

Why Altitude Hits So Hard

At elevation, your body is forced to adapt fast—and sometimes it isn’t able to keep up. That’s when altitude illness can develop, ranging from mild to life-threatening ailments:

  • Acute Mountain Sickness (AMS): headache, nausea, fatigue
  • High-Altitude Pulmonary Edema (HAPE): fluid in the lungs, causing shortness of breath
  • High-Altitude Cerebral Edema (HACE): brain swelling, confusion, and potentially coma

These aren’t separate diseases so much as a continuum of worsening hypoxia. Most severe cases can start as mild symptoms and can later progress to more severe presentations. The quicker you can recognize the more subtle symptoms, the better you may be in avoding severe illness. 

What’s Happening Inside the Body?

When oxygen levels drop, the body goes into survival mode:

  • Blood vessels in the lungs constrict → raising pressure (risk of HAPE)
  • Blood vessels in the brain become leaky → swelling (risk of HACE)
  • Inflammatory and hormonal systems ramp up → causing AMS symptoms

In short: your body is trying to compensate in response to the change in environment, but sometimes those compensations backfire.

Enter Hyperbaric Oxygen Therapy (HBOT)…

Now imagine flipping the script. Instead of struggling in thin air, what if you could flood your body with oxygen under pressure? That’s exactly what Hyperbaric Oxygen Therapy (HBOT) does. Inside a pressurized chamber, you breathe 100% oxygen, dramatically increasing how much oxygen dissolves into your blood. In a way you have artificially placed yourself in a lower altitude. 

How HBOT Helps at Altitude

HBOT essentially acts like a “simulated descent”—one of the most important treatments for altitude illness.

It can:

  • Boost oxygen levels in your blood and tissues
  • Improve brain function in hypoxic states
  • Reduce inflammation and oxidative stress
  • Potentially stabilize the blood–brain barrier

In wilderness medicine and EMS settings, portable hyperbaric chambers are already used when immediate descent isn’t possible. They can be lifesaving.

But there’s a catch: The benefits are temporary. Once the pressure is removed, symptoms can return if the person is still at altitude where their symptoms first started.

A New Idea: Can HBOT Be Used Before You Climb?

Here’s where things get interesting. Researchers are now exploring whether HBOT could be used not just as treatment—but as preparation.

The concept: preconditioning

The idea is that repeated exposure to hyperbaric oxygen before ascent might “train” the body to handle low-oxygen environments better—similar to acclimatization.

Potential effects include:

  • Activation of hypoxia-response pathways (like HIF)
  • Improved mitochondrial efficiency (better energy use)
  • Increased antioxidant defenses
  • Enhanced microcirculation

In theory, this could mean: fewer symptoms, better performance, and lower risk of severe altitude illness

What Does the Evidence Say?

Early research is promising, but not definitive.

Some studies suggest:

  • Reduced incidence and severity of AMS
  • Better oxygen saturation at altitude
  • Possible protection against brain and lung edema

But there are still big unknowns:

  • What pressure and duration work best?
  • How long before ascent should HBOT be done?
  • Who benefits most—athletes, mountaineers, or everyone?

For now, HBOT preconditioning is an exciting idea—not standard practice.

What About Athletes and High Performers?

Altitude is a major challenge for:

  • Endurance athletes
  • Military personnel
  • Search and rescue teams
  • Mountaineers

Performance drops quickly due to:

  • Lower VO₂ max
  • Faster fatigue
  • Impaired decision-making

HBOT might help by:

  • Improving oxygen efficiency
  • Preserving cognitive function
  • Delaying fatigue

But again—this is still being studied, and access to HBOT can be limited and expensive.

How Does HBOT Compare to Proven Strategies?

Right now, the gold standard hasn’t changed:

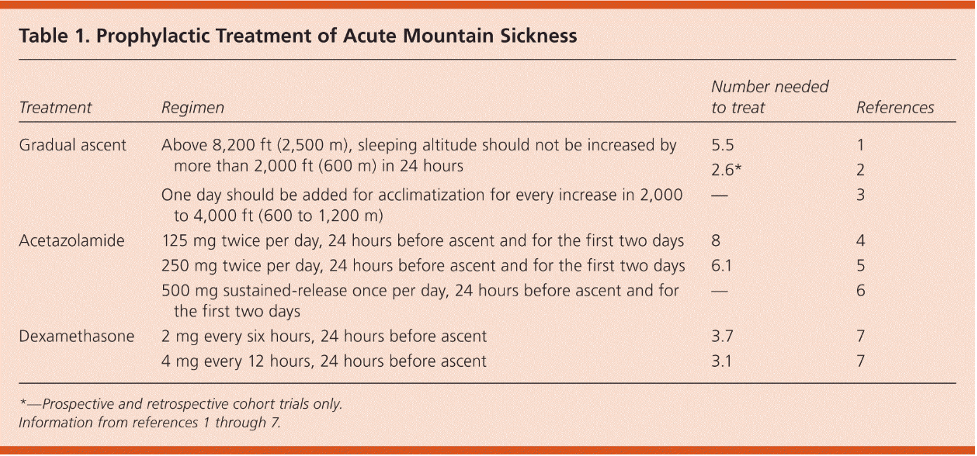
  • Gradual ascent → still the most effective prevention
  • Acetazolamide → helps your body acclimate faster
  • Dexamethasone → used in higher-risk situations

HBOT (for prevention) is still catching up in terms of evidence.

Is HBOT Risk-Free?

Not entirely. While generally safe, it can cause: ear or lung barotrauma (due to pressure-related injury), oxygen toxicity (rare but serious), and can lead to increased oxidative stress with overuse. These risks matter more when using HBOT proactively rather than as a rescue therapy.

Where This Is Headed

HBOT sits at a fascinating intersection of performance, medicine, and physiology.

Future research is looking to focus on finding optimal preconditioning protocols like treatment duration and number of set times. Some other areas also include identifying which patient populations would benefit most from this form of treatment and combining HBOT with other strategies like hypoxic training.

Bottom Line…

Hyperbaric oxygen therapy is already a powerful tool for treating severe altitude illness, especially when descent from altitude isn’t immediately possible.

As a preventive strategy, it shows real promise, but it’s not ready to replace the fundamentals.

For now, your best defense at altitude is still:

  • Climb gradually
  • Know the symptoms and have a buddy!
  • Use proven medications when appropriate (like Acetazolamide)

HBOT may one day become part of the toolkit—but for now, it’s a high-potential frontier, not a first-line solution.

Centers for Disease Control and Prevention. (2023). High-altitude travel and altitude illness. https://www.cdc.gov/travel/page/high-altitude-travel

National Center for Biotechnology Information. (2023). High-altitude illness. In StatPearls. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK430716/

National Center for Biotechnology Information. (2023). Hyperbaric oxygen therapy. In StatPearls. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK459172/

PubMed Central. (2020). Hyperbaric oxygen therapy: Mechanisms and clinical applications. https://www.ncbi.nlm.nih.gov/pmc/articles/PMCPubMed Central. (2018). Pathophysiology, prevention, and treatment of high-altitude illness. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC

Wilderness Medical Society. (2019). Wilderness Medical Society clinical practice guidelines for the prevention and treatment of acute altitude illness. Wilderness & Environmental Medicine, 30(4), S3–S18. https://doi.org/10.1016/j.wem.2019.04.006

Hackett, Peter H., & Roach, Robert C.. (2001). High-altitude illness. New England Journal of Medicine, 345(2), 107–114. https://doi.org/10.1056/NEJM200107123450206

Bärtsch, Peter, & Swenson, Erik R.. (2013). Acute high-altitude illnesses. New England Journal of Medicine, 368(24), 2294–2302. https://doi.org/10.1056/NEJMra1214870

Moon, Richard E.. (2019). Hyperbaric oxygen therapy indications. Undersea & Hyperbaric Medicine, 46(3), 425–430.

Milledge, James S., West, John B., & Schoene, Robert B.. (2013). High altitude medicine and physiology (5th ed.). CRC Press.

Peak Performance: Coach wants a Blood Test

Iron Deficiency without Anemia in Individuals Living at Altitude 

Madeline Larson, PA-S2

People living at high altitude typically have higher hemoglobin levels compared to those at sea level. This physiological adaptation occurs due to the lower oxygen availability at high elevations which stimulates the production of erythropoietin, a hormone that prompts the bone marrow to produce more red blood cells made famous by the Lance Armstrong blood-doping scandal. Hemoglobin, the protein in red blood cells that carries oxygen, thus increases to enhance the blood’s oxygen-carrying capacity. This adaptation helps individuals efficiently transport oxygen to tissues despite the reduced atmospheric pressure. Over time, this increased hemoglobin level helps maintain adequate oxygen delivery to vital organs, supporting overall health and physical performance in the challenging high-altitude environment.

Despite this natural adaptation of increased hemoglobin levels, people living at high altitude are still susceptible to anemia. Chronic exposure to lower oxygen levels can sometimes lead to a condition where the body’s capacity to produce red blood cells is insufficient to meet increased demands. This can be due to various factors, including inadequate dietary iron, vitamin deficiencies, or underlying health conditions that impair red blood cell production or lifespan. Additionally, individuals who move to high altitudes without sufficient acclimatization may experience a temporary drop in hemoglobin levels until their bodies adjust. Addressing anemia in such environments often involves a combination of dietary adjustments, supplementation, and medical interventions to ensure that the red blood cell count remains adequate to maintain optimal oxygen transport and overall health.

In people living at high altitudes, the threshold for diagnosing anemia is often adjusted to account for the lower oxygen levels in the environment. At high altitudes, the normal range for hemoglobin and hematocrit levels can be higher due to the body’s adaptation to reduced oxygen levels.

For example:

  • Hemoglobin Threshold: At sea level, anemia is commonly defined as a hemoglobin level below 13.0 grams per deciliter (g/dL) in men and 12.0 g/dL in women. In high-altitude areas, these thresholds might be higher. For instance, at elevations above 2,500 meters (8,200 feet), a hemoglobin level of around 14.0 g/dL in men and 13.0 g/dL in women might be considered the lower limit of normal.
  • Hematocrit Threshold: Similarly, normal hematocrit levels are adjusted. At sea level, anemia is typically diagnosed with hematocrit levels below 39% in men and 36% in women. At high altitudes, these values might be adjusted to about 42% for men and 40% for women.

These adjustments are necessary because high-altitude residents tend to have higher hemoglobin and hematocrit levels as a physiological response to lower oxygen availability. If someone at high altitude presents with symptoms of anemia but has hemoglobin or hematocrit levels within the high-altitude normal range, further evaluation might be needed to assess their overall health and adapt to the specific altitude.

Understanding Iron Deficiency Without Anemia: What You Need to Know

Iron is an essential mineral that plays a crucial role in various bodily functions, most notably in the production of hemoglobin, which is vital for oxygen transport in the blood. While many people are familiar with iron deficiency anemia, where low iron levels lead to a reduced number of red blood cells, there is another, often overlooked, condition: iron deficiency without anemia. Understanding this condition is important for addressing health issues that can arise even in the absence of anemia. 

What is Iron Deficiency Without Anemia?

Iron deficiency without anemia occurs when the body’s iron levels are insufficient, but the quantity of red blood cells and their capacity to carry oxygen remain within normal ranges. Essentially, it’s a state where iron stores are low, but the body has not yet progressed to a point where anemia develops. This can make it a bit tricky to diagnose since standard blood tests for anemia might not immediately show abnormalities.

Symptoms and Effects

The symptoms of iron deficiency without anemia can be subtle and may vary from person to person. Common signs include:

  • Fatigue and Weakness: Even without anemia, low iron can lead to feelings of tiredness and decreased energy levels. Coaches notice that some competitive athletes benefit from addressing iron deficiency without anemia.
  • Frequent Headaches: Iron is involved in various enzymatic processes in the body, and a deficiency might contribute to headaches or migraines.
  • Cold Hands and Feet: Poor circulation or lower iron levels can result in feeling unusually cold.
  • Brittle Nails and Hair: Iron deficiency can affect the health and strength of nails and hair.
  • Restless Legs Syndrome: Some people with low iron levels experience uncomfortable sensations in their legs, particularly at night.

Causes of Iron Deficiency Without Anemia

Several factors can contribute to iron deficiency without leading to anemia:

  • Dietary Intake: Inadequate consumption of iron-rich foods, such as red meat, legumes, and fortified cereals, can lead to low iron levels.
  • Increased Iron Requirements: Certain life stages and conditions, such as pregnancy, heavy menstrual periods, or intense physical activity, can increase iron needs.
  • Absorption Issues: Conditions like celiac disease or inflammatory bowel disease can impair iron absorption.
  • Chronic Inflammation: Chronic illnesses or inflammatory conditions can affect iron metabolism and utilization, even if anemia does not develop.

Diagnosis and Testing

Diagnosing iron deficiency without anemia typically involves a combination of tests and assessments:

  • Serum Ferritin Levels: Ferritin is a protein that stores iron in the body. Low levels can indicate depleted iron stores, even if anemia is not present.
  • Serum Iron and Transferrin Saturation: These tests measure the amount of circulating iron and how well it is being transported in the blood.
  • Complete Blood Count (CBC): While a normal CBC might not show anemia, it can help rule out other conditions.

Treatment and Management

Addressing iron deficiency without anemia often involves dietary and lifestyle changes:

  • Iron-Rich Diet: Incorporate foods high in iron, such as lean meats, leafy green vegetables, nuts, and seeds. Iron from animal sources (heme iron) is generally more easily absorbed than plant-based iron (non-heme iron).
  • Vitamin C Intake: Consuming vitamin C-rich foods like oranges, strawberries, and bell peppers can enhance the absorption of non-heme iron.
  • Iron Supplements: In some cases, a healthcare provider may recommend iron supplements. It’s important to follow dosing instructions carefully, as excessive iron intake can have adverse effects.
  • Address Underlying Causes: If an underlying condition is contributing to iron deficiency, treating that condition is crucial for resolving the deficiency.

Conclusion

While long-term adaptation to high altitude allows individuals to increase their iron available for erythropoiesis due to higher demand, those who have not adapted or are vulnerable due to exercise or pregnancy, are at risk of depleting their iron stores. Iron deficiency without anemia is a condition that requires attention to prevent potential health issues and improve overall well-being. 

Resources & References:

Alkhaldy HY, Hadi RA, Alghamdi KA, Alqahtani SM, Al Jabbar ISH, Al Ghamdi IS, Bakheet OSE, Saleh RAM, Shehata SF, Aziz S. The pattern of iron deficiency with and without anemia among medical college girl students in high altitude southern Saudi Arabia. J Family Med Prim Care. 2020 Sep 30;9(9):5018-5025. doi: 10.4103/jfmpc.jfmpc_730_20. PMID: 33209838; PMCID: PMC7652112.

Kaylee Sarna, Gary M Brittenham, Cynthia M Beall, Detecting anaemia at high altitude, Evolution, Medicine, and Public Health, Volume 2020, Issue 1, 2020, Pages 68–69, https://doi.org/10.1093/emph/eoaa011

Martina U. Muckenthaler, Heimo Mairbäurl, and Max Gassmann. Iron metabolism in high-altitude residents. 2020 Jan 9: https://journals.physiology.org/doi/pdf/10.1152/japplphysiol.00019.2020

PORTRAIT OF A HIGH-ALTITUDE ATHLETE: THE ULTRA MOUNTAIN ATHLETE, 2.0

Six years ago, I sat down with ultra mountain athlete Yuki Ikeda for the first time for an interview about his experience training, competing and recovering in the extreme altitudes of Colorado’s central Rocky Mountains. At the time, Yuki had only recently started competing in running races at over 10,000′ (3048m) since beginning his career as a cyclist in 2003, going pro in 2007.

In 2019, he managed to compete in his first Leadville Race Series, which included 50- and 100-mile MTB and trail run courses starting at above 10,000′ and rising to over 12,000′.

This summer, I had the pleasure of catching up with this extraordinary athlete and his wife Sayako, a dietitian and high-altitude runner herself who inspired Yuki to compete as a runner as well as a cyclist. The pair have been spending summers in the Colorado high country every year to train and compete before returning to their home in Japan to continue competing year-round, and between their experience training and racing and nutritional expertise, they make a formidable team.

Six years ago, we were all three of us in our thirties, and when I asked about what has changed about training and acclimating to the altitude since then, there was certainly a consensus about how it hasn’t gotten easier now that we are all in our forties. A significant part of their strategy for success has always been nutrition, and at this elevation, maximizing the delivery of oxygen throughout the body makes a huge difference. In our last interview, Yuki talked about incorporating foods rich in nitrates, which facilitate your body’s production of nitric oxide, like red bell peppers, arugula and beets, and these are still a big part of their diet.

Something they’ve been paying closer attention to lately is iron, also a critical component of blood. It’s dangerous for iron levels to be too high, but it can be a critical supplement for healthy circulation. In the case of long distance runners, blood vessels can take a considerable beating as feet hit ground over and over again for long periods of time. One food in particular that contains a high level of iron is clams. In Japan and the Pacific, asari, also known as Manila clam or Japanese cockle, is a regular part of cuisine and easy to find. Here in the middle of the Rockies, however, Yuki and Sayako have been buying canned clams to supplement their iron.

Every summer, the couple have come to the Colorado Rockies to train and compete. They’re full-time residence is in Tokyo, Japan, so each time they are traveling from sea-level, a dramatic and quick ascent to a high elevation. The decrease in available oxygen in the air at high altitude prompts a response in the body to create more red blood cells in order to carry more oxygen throughout the body. This requires more iron, which is vital for this process.

Additionally, the two athletes are paying special attention to nutrient absorption. Most of their diet is plant-based, and until recently, Yuki has been eating a completely vegan diet. Organic compounds found in plants called tannins and polyphenols — while beneficial — can inhibit your body’s absorption of nutrients you eat by up to 90%. So consuming something with these compounds along with your meal may dramatically decrease the benefits of nutrition in the food you’re eating. Coffee contains these compounds, so Sayako recommends waiting at least an hour after a meal to have a cup of coffee in order to maximize nutrient uptake. Even better, vitamin C can enable greater absorption, so consuming it (even in other foods such as a citrus) with a meal can be very helpful.

“… iron is also necessary for the hypoxia-inducible-factor (HIF) pathway, cellular energy production, myoglobin function (the muscle oxygen acceptor), and thyroid hormone function,” write DeLoughery and DeLoughery in a recent article for the Wilderness Medical Society. “The HIF pathway is the key regulator of the body’s response to hypoxia. Typically, the HIF-1 and HIF-2 proteins are rapidly degraded, but they are stabilized by hypoxic conditions when prolyl hydroxylase, which tags the HIFp roteins for degradation, is inhibited. When stabilized, the HIF proteins function as transcription factors that coordinate the synthesis of various proteins essential for the body’s response to hypoxia. Prolyl hydroxylase requires iron to function, and with a low iron level, this is less effective, leading to an exaggerated response to hypoxia.”

It is also important to note that, as Yuki and Sayako point out, it can take three to four weeks for anyone to experience noticeable results from any change in diet and nutrition. Keeping this in mind, it is advisable to increase iron intake weeks ahead of a trip to a high altitude environment, although further research may be needed to recommend just how much.

DeLoughery, MD, Emma P. Emma P. DeLoughery, MD and Thomas G. DeLoughery, MD, “Women, Iron, and Altitude — Path to the Peak”, Wilderness Medical Society 2025.

KYRGYZSTAN VS SUMMIT COUNTY, COLORADO: EXERCISE AT ALTITUDE

How does the low oxygen environment at altitude affect our ability to exercise?  What is the risk for developing harmful changes in the heart and lungs? Does sleep apnea contribute to these risks? Can supplemental oxygen reverse or reduce these risks and increase our exercise ability at altitude?

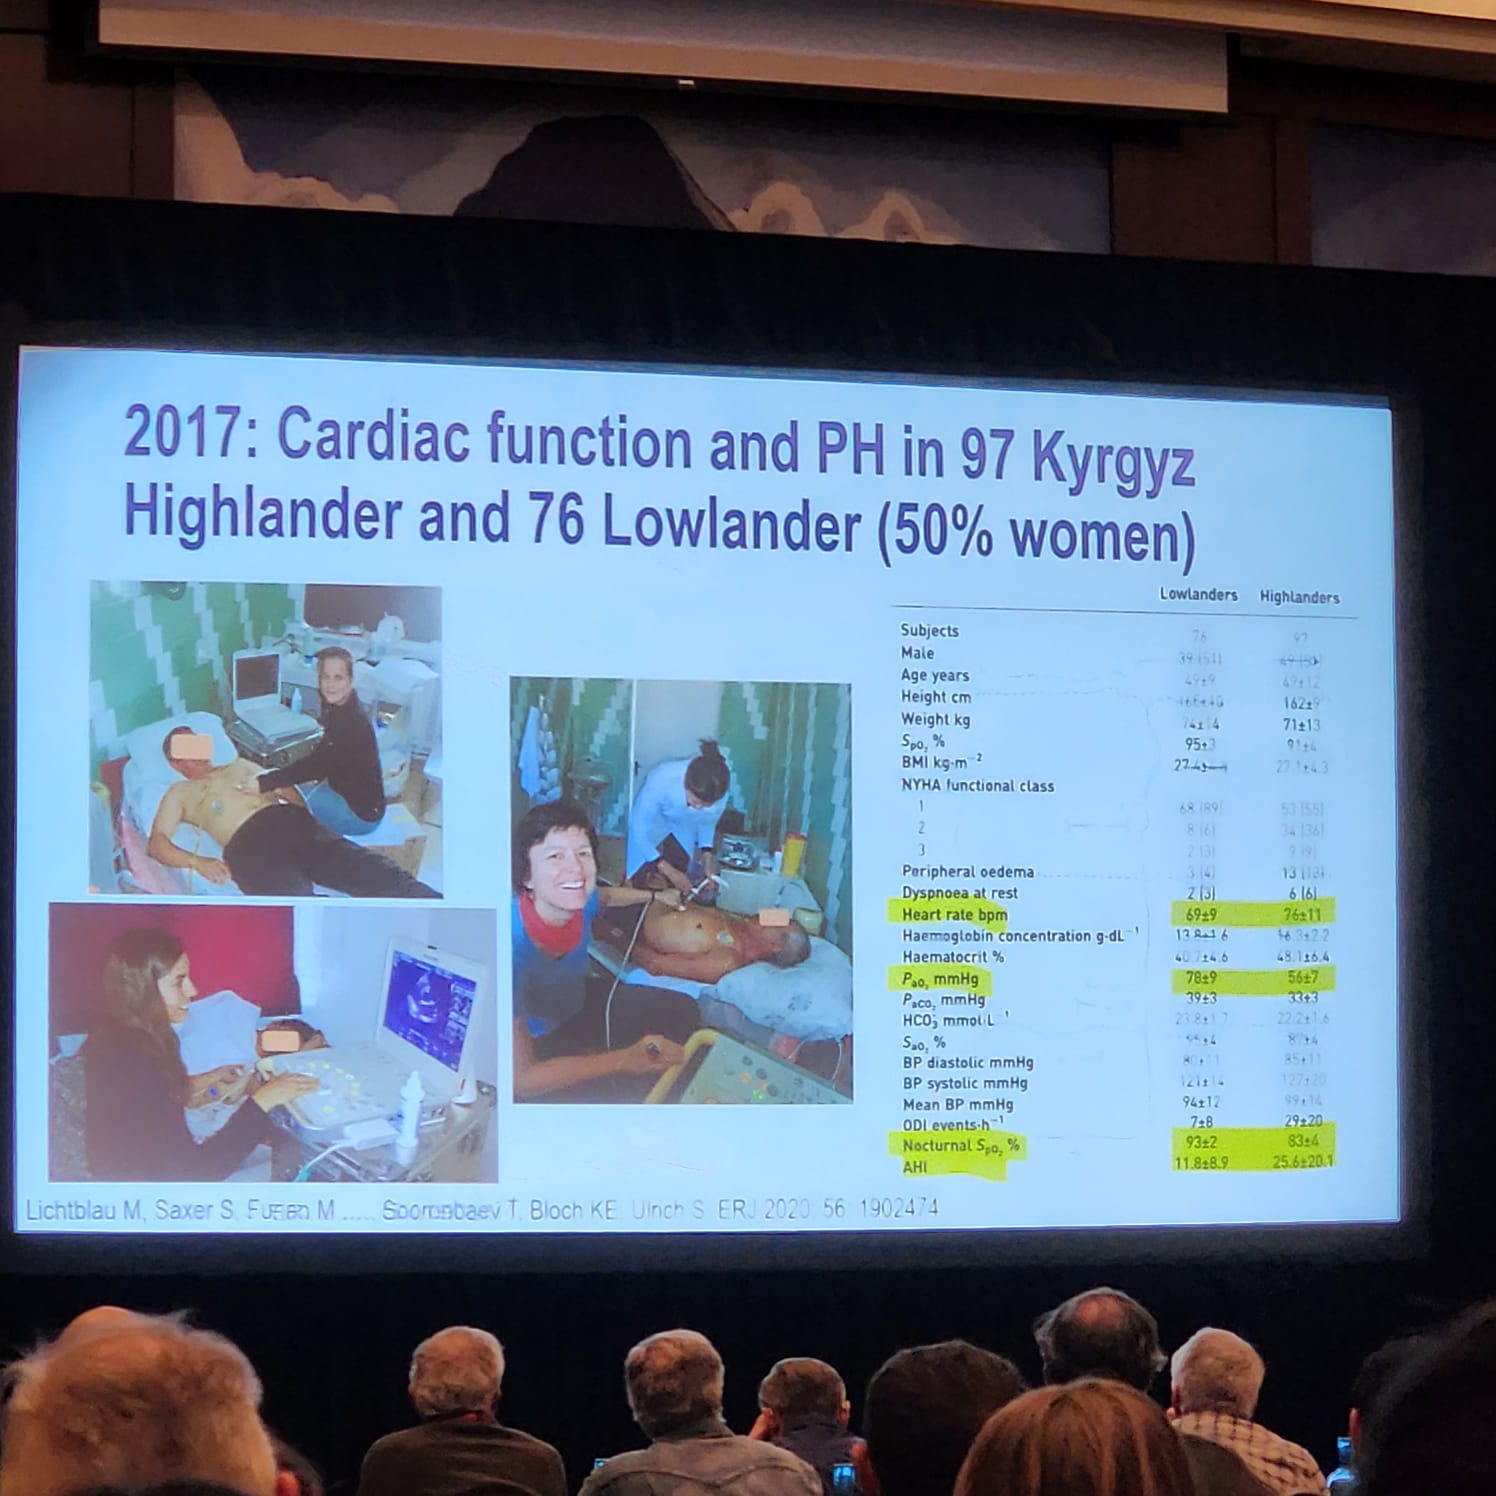
An audience of conference participants sit observing a slide in a presentation reading "Cardiac function and PH in 97 Kyrgyz Highlander and 76 Lowlander (50% women).

These important questions have been studied by an international research team conducting tests on residents of the Tien Shan mountain range in Kyrgyzstan, 2500-3500 m (8,200 to 11,482 feet). Dr. Silvia Ulrich presented some of their findings at the Hypoxia 2025 conference in Lake Louise in the Canadian Rocky Mountains this past winter. Using an exercise bike they measured ECG, pulmonary gas exchange and oxygen saturation in healthy highlanders. Participants’ average age was 48 years, 46 % were women, and their average oxygen saturation (SpO2) at rest was 88%. Normal occupations include nomadic herdsmen, hunters and soldiers who usually travel by car or horse, with no prior experience cycling or running. An echocardiogram was performed to assess pulmonary artery pressures (PAP) and right heart function.

Arterial blood gas analysis at baseline showed a normal pH, low oxygen, mildly decreased carbon dioxide and bicarbonate, and higher hemoglobin concentrations. Bicarbonate values were 22-26 moles/L. In Summit county, in the Rocky Mountains of Colorado, with residents living between 2500 to 3300 m bicarbonate values are 17-20 moles/L.

Results showed their peak oxygen uptake, and peak work rate was reduced by one quarter compared to predicted values for lowlanders. Oxygen saturation decreased during exercise. “Exercise limitation was related to an exercise -induced worsening of hypoxemia, high ventilation equivalents for oxygen uptake and carbon dioxide output, a reduced external work efficiency and a lower peak heart rate than predicted for age.” (1) In other words, they had to breathe harder to maintain their oxygen and carbon dioxide at normal values and use more effort for the same musculoskeletal output. Their heart rate did not increase as much as a person from lower altitude doing the same work.

There is little research on exercise capacity in long-term residents at altitude.  Most studies focus on athletes or comparing healthy acclimatized men to recent arrivals. The hypoxic environment is a known risk for pulmonary hypertension, which can lead to exercise intolerance and fatigue that is reversible with descent or oxygen use when diagnosed in a timely manner. Sleep apnea with the accompanying hypoxic episodes adds to this risk. Summit County residents show improvement in both systemic and pulmonary hypertension with supplemental oxygen during sleep, according to local health care providers.

Kyrgyzstan residents studied showed a strong correlation between  the incidence of sleep apnea with hypoxia (time below 90% SpO2), and abnormal pulmonary artery pressures. Echocardiograms compared 97 highlanders with 76 lowlanders who were asymptomatic. Between 6% and 35% had increased PAP depending on which definition is used. 

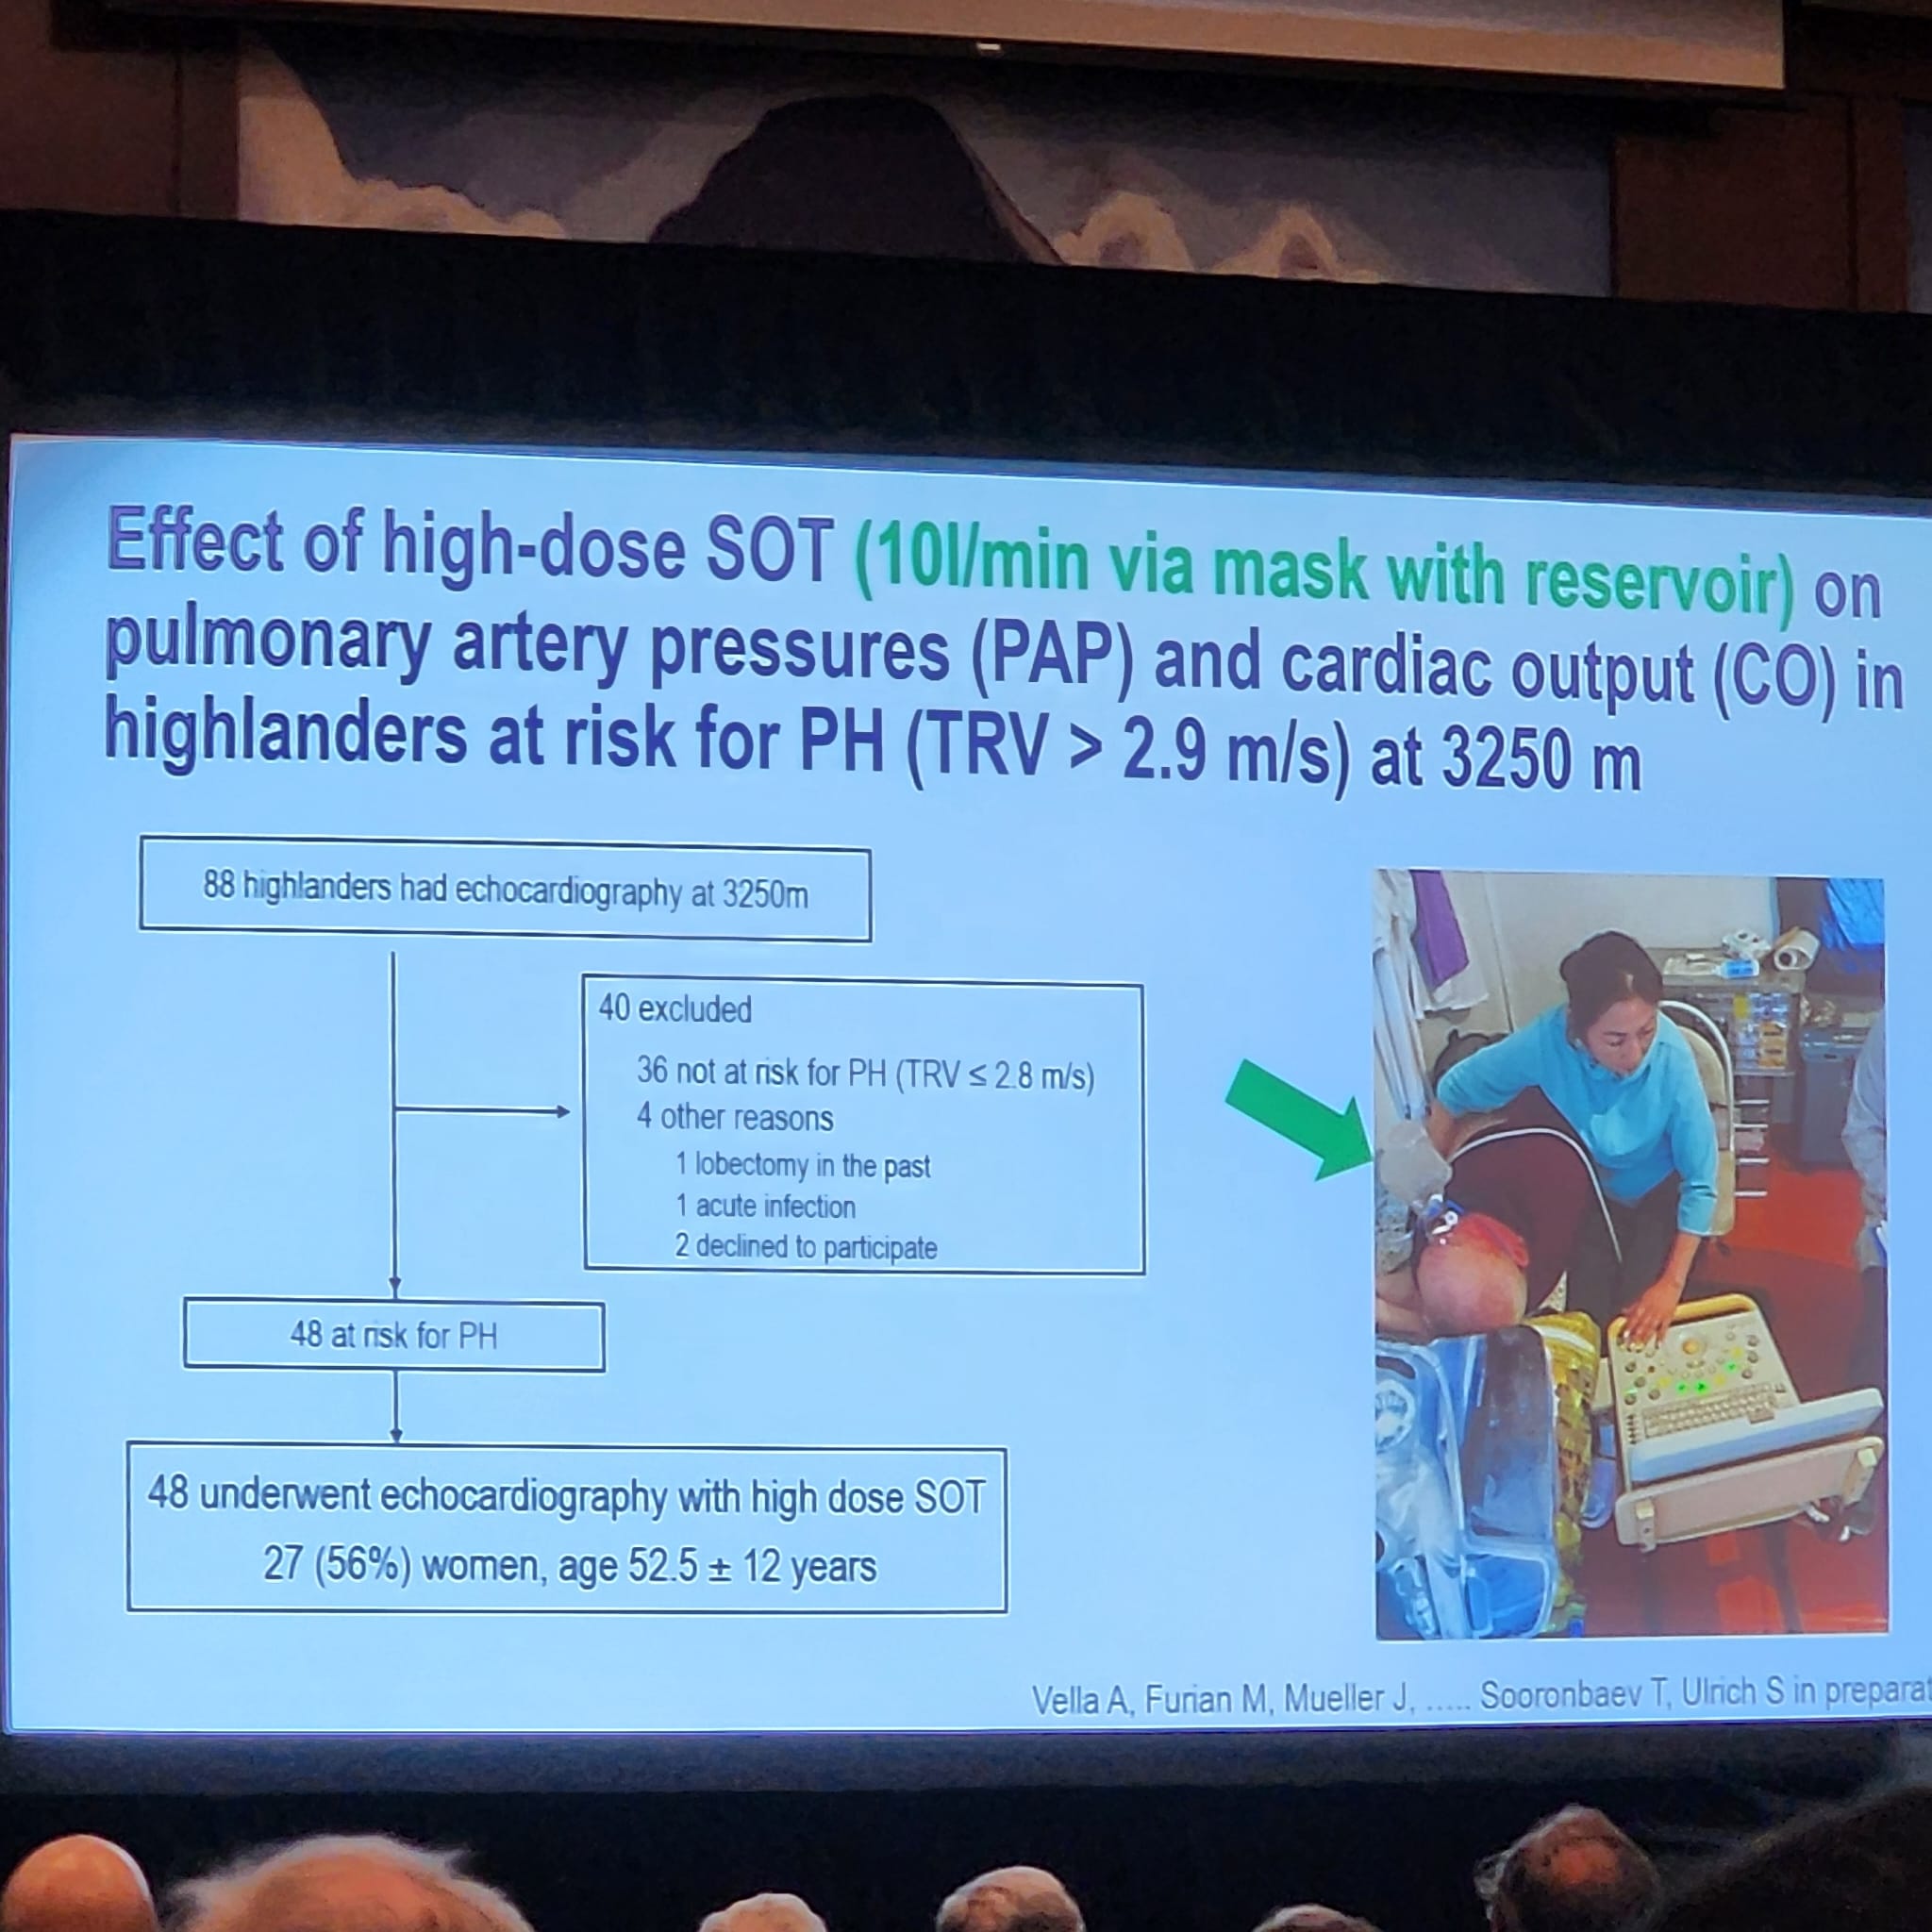
A slide at a conference presentation on the effect of high-dose SOT on pulmonary artery pressures and cardiac output in highlanders at risk for PH at 3250 meters.

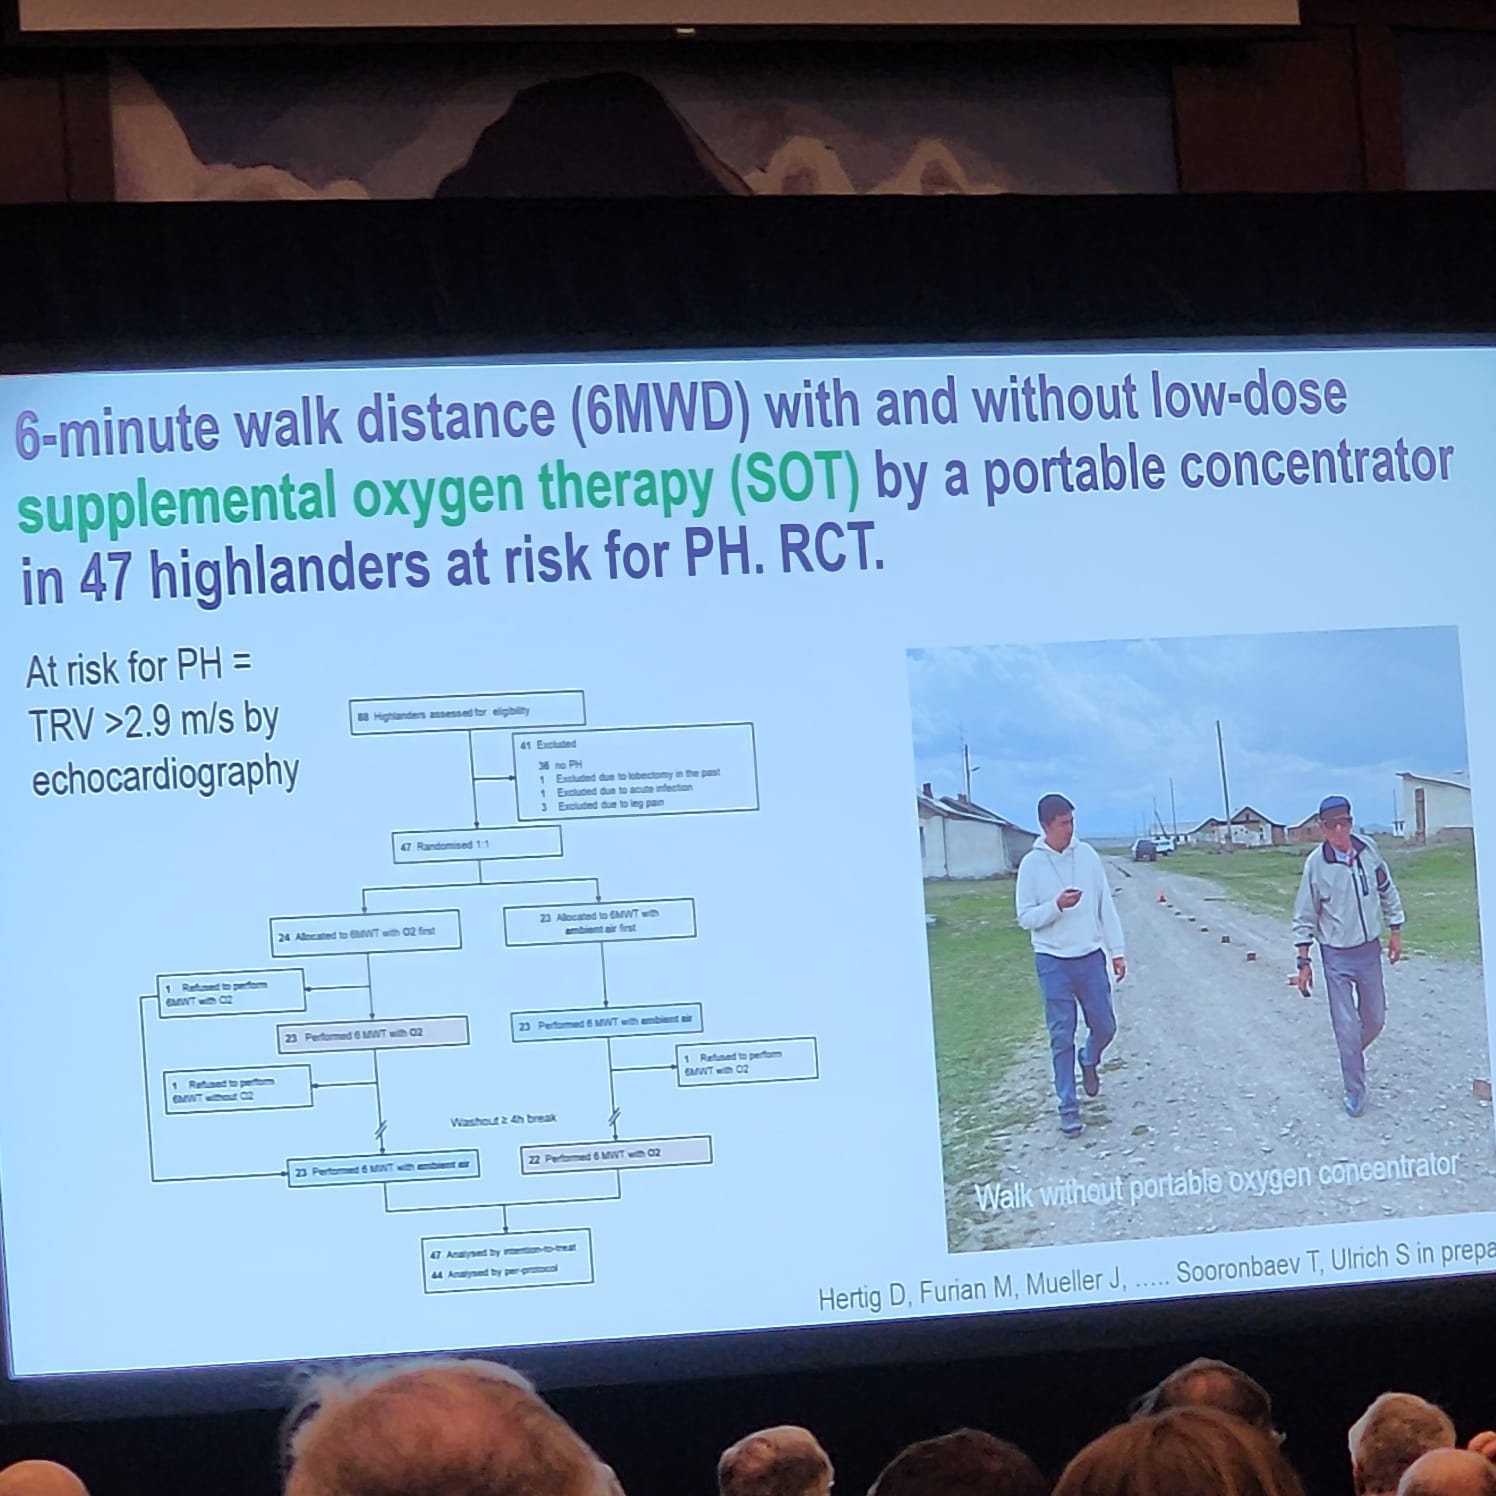
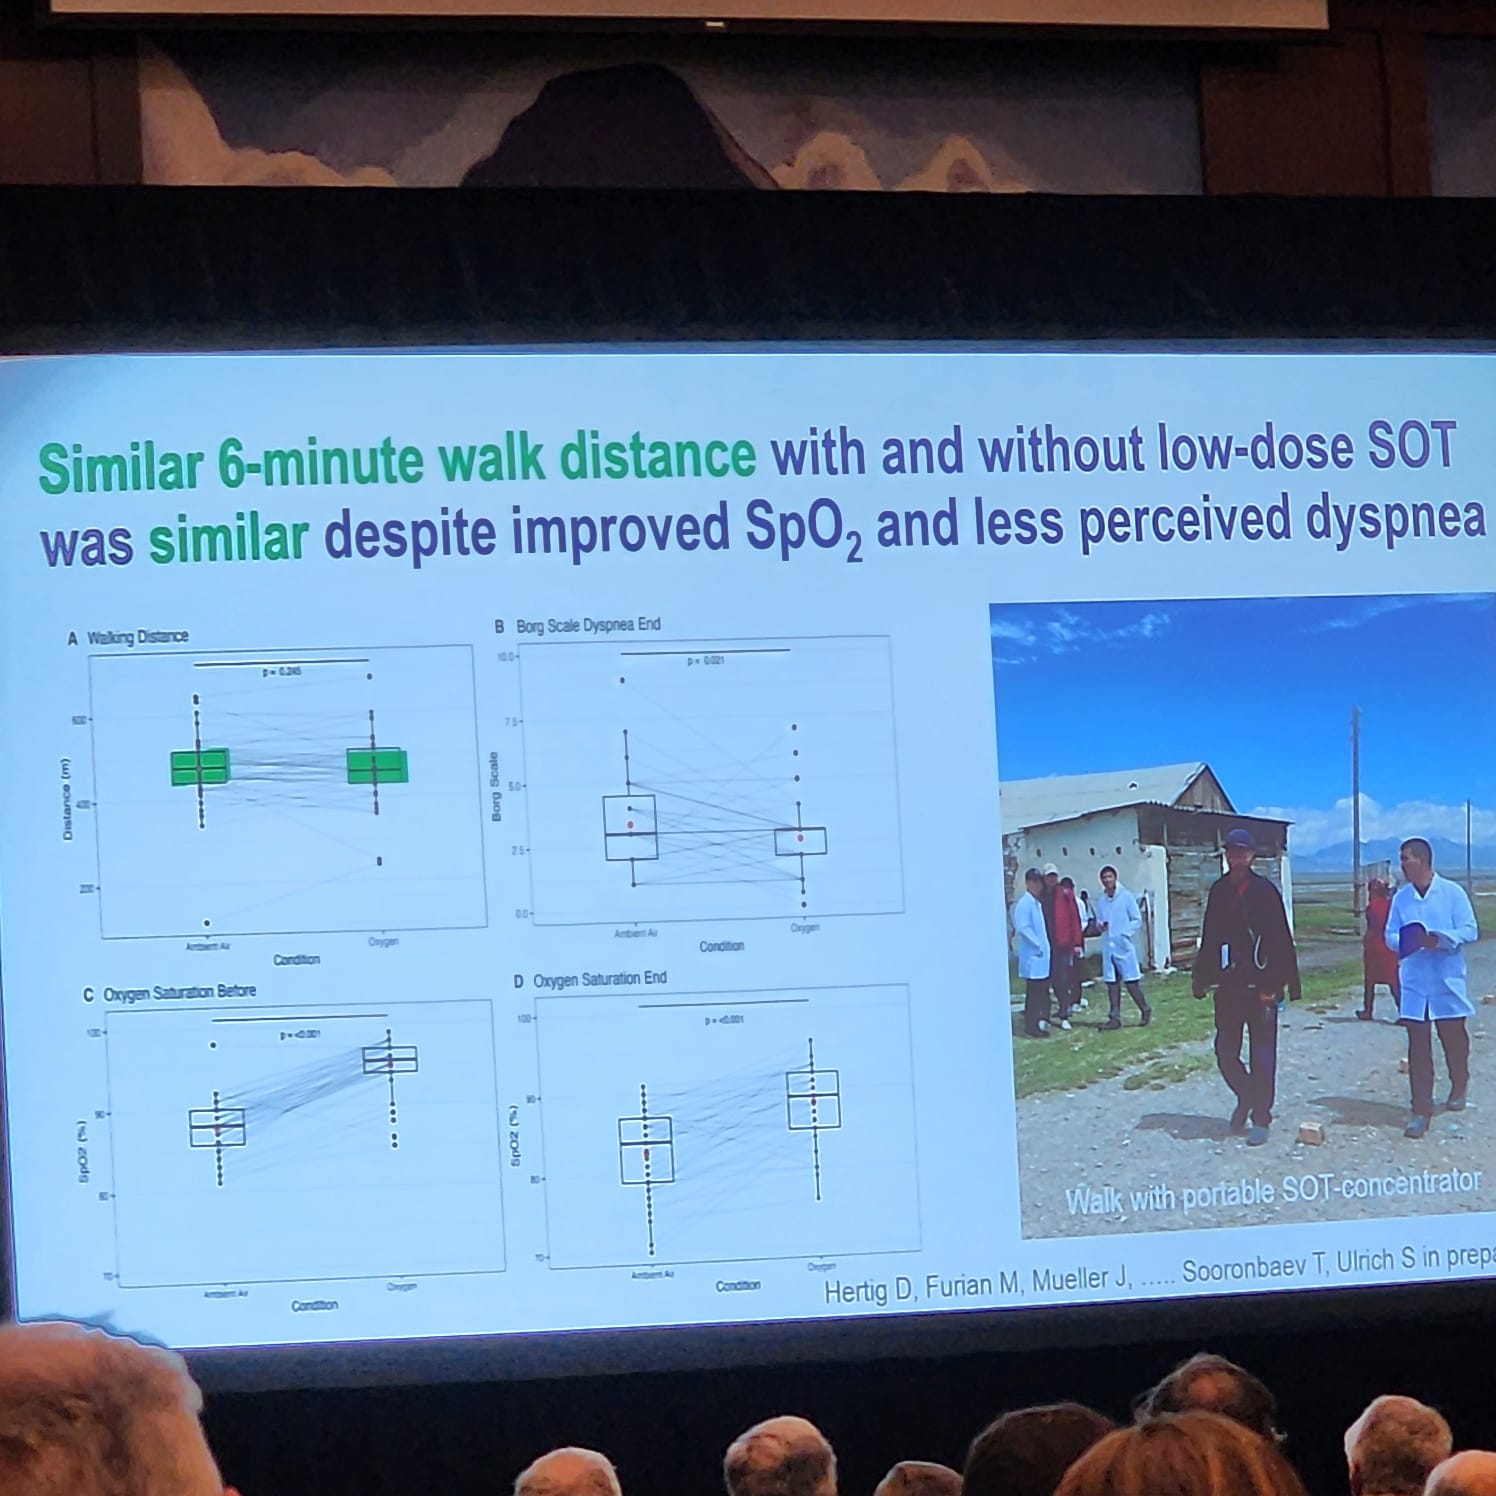
The research team also evaluated their response to supplemental oxygen at altitude and 760m elevation using the six minute walk test. Although the test subjects reported less shortness of breath and had higher measured oxygen levels they were not able to walk further. Supplemental oxygen did reduce pulmonary artery pressures in those at risk when tested at 3,200 m.

A slide from a presentation on an experiment where oxygen levels in residents of high altitude in Kyrgyzstan are measured during a 6-minute walk.

This research was conducted by a crew of scientists who brought all the equipment with them to a basic medical clinic in a village.

Summit County cardiologist Warren Johnson was impressed by the numbers of people with elevated pressures in their lungs. “It could be as high as 30 per cent of adults,” he told local physicians. Symptoms are subtle: decreased exercise tolerance, mild shortness of breath, trouble sleeping, high red blood cell counts. Most people just think they are out of condition or aging.

A study in Spiti Valley India of residents living at 9000-13000 ft found an incidence of three per cent with PH.  Dr Johnson suspects this is a highly adapted population with centuries of mountain living.

Diagnosing this condition early with Echocardiogram can prevent serious disability.  Treatment is as simple as sleeping on oxygen. These measurements and much more are performed on a daily basis at the St. Anthony Summit Hospital, a 34-bed hospital serving five counties in Colorado, located at 2800 m. A parallel study to establish baseline normal values for the healthy population and identify the risk for pulmonary hypertension in asymptomatic mountain residents would be valuable for health care providers who are frequently asked to counsel residents on the risk of living at altitude.

Forrer A, Scheiwiller PM, Mademilov M, Lichtblau M, Sheraliev U, Marazhapov NH, Saxer S, Bader P, Appenzeller P, Aydaralieva S, Muratbekova A, Sooronbaev TM, Ulrich S, Bloch KE, Furian M. Exercise Performance in Central Asian Highlanders: A Cross-Sectional Study. High Alt Med Biol. 2021 Dec;22(4):386-394. doi: 10.1089/ham.2020.0211. Epub 2021 Aug 24. PMID: 34432548.

Lichtblau M, Saxer S, Furian M, Mayer L, Bader PR, Scheiwiller PM, Mademilov M, Sheraliev U, Tanner FC, Sooronbaev TM, Bloch KE, Ulrich S. Cardiac function and pulmonary hypertension in Central Asian highlanders at 3250 m. Eur Respir J. 2020 Aug 20;56(2):1902474. doi: 10.1183/13993003.02474-2019. PMID: 32430419.

Thin Air Making You Lightheaded?

by Joy Plutowski, PA-S2

Feeling lightheaded after going to a high altitude is a key symptom of acute mountain sickness (AMS)—a condition caused by the reduced oxygen available in thin mountain air. AMS often comes with other symptoms like headache, nausea, and fatigue, usually starting after a recent climb to higher elevations.

But what if it’s not just AMS? For people with conditions like postural orthostatic tachycardia syndrome (POTS), which affects blood flow and heart rate, lightheadedness at altitude could be a clue to an underlying issue. While AMS happens because of low oxygen, POTS is tied to a problem with how the nervous system regulates the body. In some cases, going to altitude might even uncover undiagnosed POTS, as symptoms can become more noticeable in these conditions.

Living With POTS

Living with POTS has been a journey of adaptation, requiring constant vigilance and adjustment to manage a complex array of symptoms. Each new environment brings its own challenges, demanding a personalized approach to maintaining stability. My recent clinical rotation in Frisco, Colorado, situated at 9,000 feet above sea level, provided an invaluable opportunity to observe firsthand how altitude influences the physiology of POTS. An overnight stay in Denver for partial acclimatization helped mitigate some initial altitude-related exacerbations, but the first few days at higher elevation were marked by pronounced symptoms, including lightheadedness, tachycardia, and insomnia. Physically demanding activities, such as snowboarding, pushed my body to its limits, resulting in extreme fatigue and heightened tachycardia. Despite these challenges, I observed gradual improvement; by the second week, I had returned to my baseline—if not better than during my time in the heat of Phoenix, Arizona. Interestingly, the colder temperatures of the region seemed to offer symptomatic relief, likely through vasoconstriction that may enhance circulation. These experiences have deepened my understanding of POTS as a highly individualized condition, emphasizing the critical importance of lifestyle modifications, environmental considerations, and a patient-specific approach to management. My journey underscores how adaptability and tailored interventions can significantly improve functionality and quality of life for those navigating the complexities of this syndrome.

What is POTS?

Postural Orthostatic Tachycardia Syndrome (POTS) is a chronic condition characterized by an abnormal increase in heart rate upon standing. It is a form of dysautonomia, involving dysregulation of the autonomic nervous system, which balances the sympathetic (“fight or flight”) and parasympathetic (“rest and digest”) systems. The autonomic nervous system regulates involuntary bodily functions such as heart rate, blood pressure, and digestion. POTS primarily affects women, with symptoms often appearing in their teens or twenties. It is estimated to affect between 1 to 3 million people in the United States, though it is likely underdiagnosed due to lack of awareness. Under normal conditions, standing triggers the body to constrict blood vessels and slightly increase heart rate to counteract gravity’s effects. In POTS, this response is impaired, leading to blood pooling in the lower extremities and reduced blood flow to the brain. The exact cause of POTS is not fully understood, but it is commonly linked to viral infections, autoimmune conditions, genetic predispositions, small fiber neuropathy, impaired norepinephrine regulation, or hypovolemia (low blood volume). Notably, long-COVID, a range of long-term symptoms and conditions resulting from an acute COVID infection, is linked to POTS. Approximately 1% of patients with an acute COVID-19 infection go on to develop orthostatic intolerance (Cheshire, 2024). Studies also show that keeping up with COVID-19 vaccinations can prevent long-COVID.

The hallmark symptom of POTS is an excessive increase in heart rate of over 30 bpm quickly after standing (WP, 2024). Common symptoms include tachycardia, palpitations, dizziness, and fainting (syncope or near-syncope), brain fog, headaches, lightheadedness, and severe fatigue. Less common symptoms include nausea, bloating, abdominal discomfort, shakiness, and exercise intolerance. POTS symptoms are often worsened by factors such as dehydration, heat, prolonged standing, illness, or physical stress. Diagnosing POTS involves a tilt-table test which monitors heart rate and blood pressure during positional changes. Treatment for POTS focuses on improving symptoms and quality of life through lifestyle adjustments. Key components include hydration, increased salt intake, compression garments, graded exercise therapy, and psychological support. Medications such as Fludrocortisone or Midodrine, that both increase blood pressure, may be added if the provider deems it fit. The course of POTS varies widely; some individuals experience significant improvement with treatment, others may have persistent symptoms. Early diagnosis and a multidisciplinary approach can lead to better outcomes.

The Effect of Altitude on the Autonomic Nervous System

Altitude significantly influences the autonomic nervous system due to reduced oxygen levels and atmospheric pressure, which challenge the body’s ability to maintain homeostasis. At higher elevations, the sympathetic nervous system becomes more active, increasing heart rate and blood pressure to compensate for lower oxygen availability. This is because hypoxia alters chemoreceptor and baroreceptor function, leading to increased sympathetic excitation and decreased parasympathetic tone.

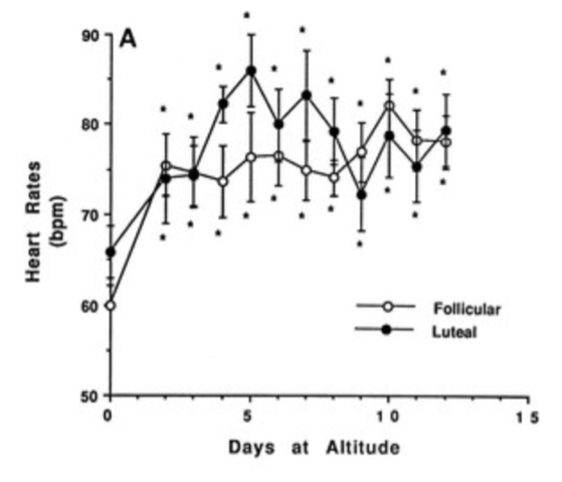
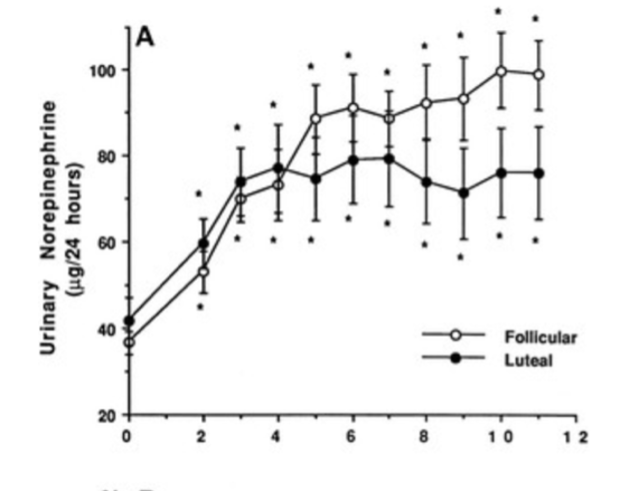
During a study at 4300 m, urine norepinephrine levels—a marker of sympathetic activity—peaked 4–6 days after altitude exposure (Mazzeo, 1998). The study compared women in different hormonal phases when exposed to high altitude. The urinary norepinephrine levels heart rates both increased over time in both follicular and luteal phases. The differences between the two were not statistically significant, showing that women experience sympathetic increase at altitude regardless of what phase of their cycle. This was done in comparison to a previous study showing the same findings in men (Mazzeo, 1998). 

A line graph indicating the rise follicular and luteal heart rates in beats per minute as days at altitude increase.
A line graph indicating increasing amounts per 24 hours of urinary norepinephrine.

Other physiological responses include increased ventilation, cardiac output, and heart rate. However, with acclimatization, heart rate and cardiac output typically return to sea-level values within 9–12 days (Hainsworth et al., 2007). Over time, improved oxygen-carrying capacity enhances tolerance to orthostatic stress. All in all, orthostatic tolerance during hypobaric hypoxia involves three mechanisms: cardiovascular control of heart rate and cardiac output, cerebrovascular responses to hypocapnic hypoxia (due to hyperventilation), and elevated sympathetic activity (Blaber et al., 2003). 

For individuals with POTS, altitude-related stresses may exacerbate symptoms. Hypoxia and reduced barometric pressure can worsen fatigue, brain fog, and dizziness by increasing the body’s effort to oxygenate tissues. Reduced oxygen delivery to the brain and tissues may intensify lightheadedness and syncope— which is already common in POTS.

Although acclimatization typically occurs within 1–2 weeks at altitude in healthy individuals, research on acclimatization in POTS patients is limited. Further studies are needed to determine whether individuals with autonomic dysfunction can adapt as effectively as those without.

Living With POTS at Altitude 

Living with POTS at altitude presents unique challenges that require careful management, as patients may find it harder to adapt to the altitude-induced changes in blood oxygenation and pressure regulation. These challenges are compounded by the existing difficulties they face in maintaining autonomic stability. The reduced oxygen levels and increased demands on the cardiovascular system can amplify POTS symptoms, making daily activities more difficult. Patients with POTS generally understand their triggers and have a protocol that was formulated with their provider. Such strategies include staying well-hydrated, using compression garments, increasing salt intake, decreasing alcohol and caffeine consumption, and avoiding sudden changes in posture. Also, gradual exposure to altitude helps the body adapt to the reduced oxygen and barometric pressure, minimizing symptom flares. For individuals with POTS visiting high-altitude environments, strict adherence to their treatment regimen, including lifestyle modifications and potentially pharmacologic interventions, is paramount for managing their condition effectively.

Blaber AP, Hartley T, Pretorius PJ (2003) Effect of acute exposure to 3,660 m altitude on orthostatic responses and tolerance. J Appl Physiol 95:591–601

Cheshire WP. (2024) Postural tachycardia syndrome. UpToDate. 

Hainsworth, R., Drinkhill, M. J., & Rivera-Chira, M. (2007). The autonomic nervous system at high altitude. Clinical autonomic research : official journal of the Clinical Autonomic Research Society, 17(1), 13–19

Mazzeo RS, Child A, Butterfield GE, et al. (1998) Catecholamine response during 12  days of high-altitude exposure (4,300 m) in women. J Appl Physiol 84:1151–1157

Doc Talk: Physician Altitude Experts on High Altitude Pulmonary Edema (HAPE)

One of our students recently came across a comprehensive publication on high altitude pulmonary edema (HAPE) on reputable point-of-care clinical resource UpToDate.com1, citing Christine Ebert-Santos, MD, MPS, the founder of highaltitudehealth.com.

Emergency medicine physician at Aspen Valley Hospital and medical director for Mountain Rescue Aspen since 1997 Dr. Scott A. Gallagher2 and emergency physician and altitude research pioneer Dr. Peter Hackett3 introduce the resource warning, “Anyone who travels to high altitude, whether a recreational hiker, skier, mountain climber, soldier, or worker, is at risk of developing high-altitude illness.”

Ebert-Santos’s (known affectionately to her patients and mountain community as “Dr. Chris”) own research is referenced in the article’s discussion of epidemiology and risk factors noting an additional category of HAPE among “children living at altitude who develop pulmonary edema with respiratory infection but without change in altitude,”4 whereas the two other recognized categories (classic HAPE and re-entry HAPE) typically happen in response to a change in altitude.

The article continues with figures illustrating how ascending too quickly or too much can dramatically increase risk: “HAPE generally occurs above 2500 meters (8000 feet) and is uncommon below 3000 meters (10,000 feet) … The risk depends upon individual susceptibility, altitude attained, rate of ascent, and time spent at high altitude. in those without a history of HAPE, the incidence is 0.2 percent with ascent to 4500 meters (14,800 feet) over four days but 6 percept when ascent occurs over one to two days. In those with a history of HAPE, recurrence is 60 percent with an ascent to 4500 meters over two days. At 5500 meters (18,000 feet), the incidence ranges between 2 and 15 percent, again depending upon rate of ascent.”

Dr. Chris discusses her experience treating her pediatric patients at high altitude in more depth in an interview with pediatric emergency medicine physician Dr. Alison Brent from Colorado Children’s Hospital for the podcast Charting Pediatrics.

Dr. Gallagher and Dr. Hackett’s article is available on UpToDate with a subscription.

  1. https://www.uptodate.com/contents/high-altitude-pulmonary-edema?source=autocomplete&index=0~1&search=HAPE ↩︎
  2. https://www.aspenhospital.org/people/scott-a-gallagher-md/ ↩︎
  3. https://www.highaltitudedoctor.org/dr-peter-hackett ↩︎
  4. Ebert-Santos, C. High-Altitude Pulmonary Edema in Mountain Community Residents. High Alt Med Biol 2017; 18:278. ↩︎

Interview with Dr. Christine Ebert-Santos on High Altitude Pulmonary Edema

by Cody Jones, Summit Daily News

“‘The first sign is usually a cough,’ Ebert-Santos said. ‘Followed by shortness of breath with any effort — even just walking — and fatigue. You just want to lie on the couch.’

If left untreated the early warning signs of high altitude pulmonary edema can rapidly progress into having fluid build up in the lungs, which will then lead to a patient’s oxygen saturation levels rapidly decreasing. If the individual does not seek treatment quickly, the condition can be fatal.”

Read the whole article here.

What is Acute Mountain Sickness?

Acute mountain sickness (AMS) is a condition that can occur when individuals ascend to high altitudes rapidly, typically above 2,500 meters (8,200 feet). The symptoms of AMS are due to the body’s struggle to adapt to the decreased oxygen levels at higher elevations. More specifically, the symptoms are caused by cerebral vasodilation that occurs in response to hypoxia, in an attempt to maintain cerebral perfusion.1

The typical symptoms of AMS include headache, nausea, vomiting, anorexia, and fatigue. In children the symptoms are less specific including increased fussiness, crying, poor feeding, disrupted sleep, and vomiting. Symptom onset is usually 6-12 hours after arrival to altitude but this can vary.

AMS affects children, adults, males and females equally, with a slight increased incidence in females. It is difficult to believe, but physical fitness does not offer protection against AMS. However, people who are obese, live at low elevation, or undergo intense activities upon arrival to elevation are at increased risk.1

Descending

Descending and decreasing altitude is a vital treatment for people with severe symptoms of AMS. By decreasing altitude there will be more oxygen in the air and symptoms will not be as severe..2 

Oxygen

Since the main cause of AMS is hypoxia, oxygen supplementation is an effective treatment when descent is not wanted or possible. Supplemental oxygen even at .5L to 1L per hour can be effective in reducing symptoms.1  It can be prescribed for short periods of time or to be used only during sleep  In the central Colorado Rockies, this may be a practical solution for “out of towners” who have traveled up to the town of Leadville (10,158’/3096m) for vacation, but in an austere environment supplemental oxygen may not be a reasonable treatment option. There should be symptomatic improvement within one hour.

Acetazolamide

Acetazolamide is a carbonic anhydrase inhibitor which causes increased secretion of sodium, potassium, bicarb, and water. This mechanism of actions lends beneficial to the treatment of AMS because it decreases the carbonic anhydrase in the brain. 3There is evidence to support the use of acetazolamide in the prevention of AMS, but minimal evidence pointing towards it’s role in treatment. Dosing is inconsistent but is usually prescribed at 125-250mg BID.

Hyperbaric Therapy

Many people consider hyperbaric chambers to be large structures in hospitals, however there are portable and lightweight hyperbaric chambers that can be used in austere environments or during expeditions. The mechanism of action of hyperbaric therapy is a simulated decrease in elevation, of approximately 2500 meters. These chambers will remove symptoms within approximately one hour of use but symptoms are likely to return. They are useful in the field but not frequently required in a hospital setting.1

  1. https://www.uptodate.com/contents/acute-mountain-sickness-and-high-altitude-cerebral-edema?search=acute%20mountain%20sickness&source=search_result&selectedTitle=1~15&usage_type=default&display_rank=1#H35
  2. https://my.clevelandclinic.org/health/diseases/15111-altitude-sickness
  3. https://www.uptodate.com/contents/acetazolamide-drug-information?search=acetazolamide%20altitude&source=search_result&selectedTitle=2~150&usage_type=default&display_rank=2#F129759